Preview

Safety and Risk of Pharmacotherapy

Advanced search

MAIN INFORMATION ABOUT THE JOURNAL

Safety and Risk of Pharmacotherapy is an open-access peer-reviewed scientific and applied research journal published both in print and online. It is the only Russian scientific journal covering safety and risks of pharmacotherapy in Russia. Founded in 1994.

Aim: to report on scientific achievements and practical experience in drug safety assurance and pharmacotherapy risk reduction.

Target audience: healthcare practitioners; clinical pharmacologists and other medical specialists; pharmacists; pharmacovigilance officers and managers in pharmaceutical companies; employees of expert bodies, preclinical and clinical trial centres, regulatory and supervisory bodies, and research institutes; lecturers and students of medical and pharmaceutical universities. For more information, see Aims and Scope section.

Founder: Federal State Budgetary Institution ‘Scientific Centre for Expert Evaluation of Medicinal Products’ of the Ministry of Health of the Russian Federation.

Publication frequency: quarterly (four issues per year).

Impact factor: the journal’s two-year RSCI impact factor is 1,103 (2025).

Geographical diversity of the Editorial Board:

  • three (3) continents,
  • ten (10) countries,
  • 17 cities

Peer-review procedure:

  • double-blind peer review,
  • a minimum of two (2) reviewers per manuscript

Key metrics:

  • fourteen (14) days from submission to the first approval (on average),
  • 151 days from submission to online publication (on average),
  • 23% of invited authors,
  • 63% of manuscripts accepted,
  • 37,000 PDF uploads in 2023

Publication fee: free of charge.

Indexing: The journal is included in Scopus (Q2, Accepted Titles May 2025), the White List of scientific journals (Level 1), the List of the State Commission for Academic Degrees and Titles (VAK) under the Ministry of Science and Higher Education of the Russian Federation (Category 1), the Russian Science Citation Index (RSCI), and the DOAJ Seal. For more information on indexing in other Russian and international databases, see the Indexing section.

Registration: The journal is registered as a mass medium by the Federal Service for Supervision of Communications, Information Technologies and Mass Communications. Certificate PI No. FS77-82932 dated 14 March 2022.

Subscription index in the Press of Russia (Pressa Rossii) catalogue and in the Ural-Press agency – 57941.

Current issue

Vol 14, No 3 (2026)
View or download the full issue PDF (Russian)

MAIN TOPIC: CURRENT APPROACHES TO INCRETIN MIMETIC PHARMACOTHERAPY: COMPARATIVE EFFICACY AND SAFETY

243-248 190
Abstract

The rapid increase in the prevalence of obesity and the rise in eating disorders require a revision of treatment approaches. Modern clinical practice supplements the therapeutic arsenal of lifestyle modification and diet therapy with next-generation medicinal products, inevitably raising issues of pharmacotherapy safety, long-term risks, and nutritional support for physicians. The interview discusses fundamental changes in diet and the role of ultraprocessed foods as a risk factor for metabolic catastrophes. The possibilities and limitations of nutrigenomics are examined, in particular in the context of polymorphisms in folate metabolism genes. Special attention is given to the safety of glucagon-like peptide-1 (GLP-1) receptor agonists: the risks of gastroparesis, sarcopenia, and micronutrient deficiency are analyzed. The paradox of sibutramine use in Russian and international clinical practice is discussed. The conversation concludes with the problem of the absence of targeted drugs for anorexia nervosa and the prospects for modulation of cannabinoid and ghrelin receptors. The treatment of nutrition-related diseases requires an interdisciplinary approach, in which pharmacological intervention is necessarily accompanied by strict nutritional control and assessment of individual genetic risks.

249-262 264
Abstract

INTRODUCTION. In the last two decades, pharmacotherapy for obesity and type 2 diabetes mellitus has evolved toward drugs that target the incretin system, such as semaglutide, a glucagon-like peptide-1 (GLP-1) receptor
agonist, and tirzepatide, a dual glucose-dependent insulinotropic polypeptide (GIP) and GLP-1 receptor agonist. Both drugs are highly effective in reducing body weight and improving glycemic control, but differences in safety
profiles necessitate comparative analysis for personalized treatment selection.
AIM. Comparative assessment of the efficacy and safety of tirzepatide and semaglutide in type 2 diabetes mellitus and obesity based on clinical trial data and post-registration pharmacovigilance, identifying key differences
in the spectrum and frequency of adverse drug reactions to develop a strategy for post-registration safety monitoring.
DISCUSSION. In clinical trials, tirzepatide was associated with greater reductions in glycated hemoglobin (in SURPASS-2, the difference ranged from –0.15% to –0.44%) and body weight (in SURMOUNT-2, –14.7% vs. –9.6%
in STEP-2) compared with semaglutide; real-world data are consistent with these findings. According to pharmacovigilance databases (VigiBase, FAERS), gastrointestinal disorders are the most frequently reported adverse
drug reactions for both agents (up to 70%), with comparable risks of serious gastrointestinal events. Tirzepatide is associated with a higher risk of vomiting, diarrhea, and constipation, whereas specific signals and adverse drug
reactions have been identified for semaglutide, including acute kidney injury, nonarteritic anterior ischemic optic neuropathy, depressive disorders, and dysesthesia.
CONCLUSIONS. Tirzepatide and semaglutide are effective in reducing glycated hemoglobin levels and body weight (more pronounced for tirzepatide). The safety profiles of the drugs are generally comparable, but differences have been identified in the spectrum of rare adverse drug reactions. Due to the heterogeneity of the design and limited sample sizes, the results of studies on the effects on the thyroid gland, bone tissue, and fertility
require confirmation in long-term prospective studies. A comprehensive approach to safety monitoring is needed, combining differentiated risk monitoring for tirzepatide and semaglutide.

263-277 231
Abstract

INTRODUCTION. The success of incretin receptor agonists has changed the standard of obesity pharmacotherapy and has stimulated both the development of incremental innovations based on existing medicinal products and the search for substances with fundamentally new mechanisms of action. Given the rapid diversification of the development portfolio, its systematic monitoring is required to forecast therapeutic horizons and to prepare the healthcare system in advance for the introduction of new approaches.

AIM. To perform a comprehensive analysis of the active portfolio of clinical developments in obesity pharmacotherapy in terms of the distribution across clinical trial phases, the types of molecular targets, the assessment of comorbidity outcomes, and the completeness of pharmacological profile disclosure.

MATERIALS AND METHODS. Data from the ClinicalTrials.gov registry were analyzed. Of 726 records of the active development portfolio, 475 active interventional studies of anti-obesity medicinal products covering 210 active substances were selected.

RESULTS. The study revealed a structural asymmetry of the portfolio: radical innovations accounted for 7.6% (16 substances) and incremental innovations for 21.0% (44), while the mechanism of action of 44.8% (94) was not disclosed. A translational barrier was identified: non-incretin medicinal products had not passed beyond phase II of clinical trials, whereas phases III–IV were dominated by agonists of glucagon-like peptide-1 (GLP-1) and glucose-dependent insulinotropic polypeptide (GIP) receptors, as well as by amylin analogues. Radical targets address the loss of muscle mass (activin type II receptor inhibitors) and the recurrence of obesity, as well as modulation of independent axes of body weight regulation: the central axis (a monoamine oxidase B inhibitor), the endocannabinoid axis, and the hepatic axis (RNA interference targeting the INHBE gene). Incremental innovations are represented by monoand multiagonists of the GLP-1, GIP, and glucagon receptors, as well as by amylin and GLP-1 co-agonists. A paradigm shift was observed: in 18.7% (89) of the studies, comorbidity outcomes served as the primary endpoint (cardiovascular outcomes, 25.8%; carbohydrate metabolism outcomes, 24.7%). The leading sponsors of late-phase developments were Eli Lilly and Novo Nordisk (90 studies). More than half of the studies (245) were concentrated in the United States. The Chinese segment (117 studies) focused on scaling up validated approaches without creating fundamentally new targets; at the same time, 26 of the 94 substances with an undisclosed mechanism of action (27.7%) are being developed under the lead sponsorship of Chinese organizations.

CONCLUSIONS. The identified translational barrier determines the medium-term prospects of obesity pharmacotherapy: in the coming years, the clinical armamentarium will be expanded primarily with multiagonists of the incretin axis and amylin analogues, whereas the need for medicinal products that preserve muscle mass and prevent obesity recurrence will remain unmet. The shift of focus toward comorbidity outcomes (the concept of obesity as a multisystem disease) requires the healthcare system to prepare for the integration of multi-target medicinal products into the standards of care for cardiovascular and metabolic complications. The high proportion of candidates with an undisclosed mechanism of action hampers comprehensive horizon scanning and strategic planning.

278-289 936
Abstract

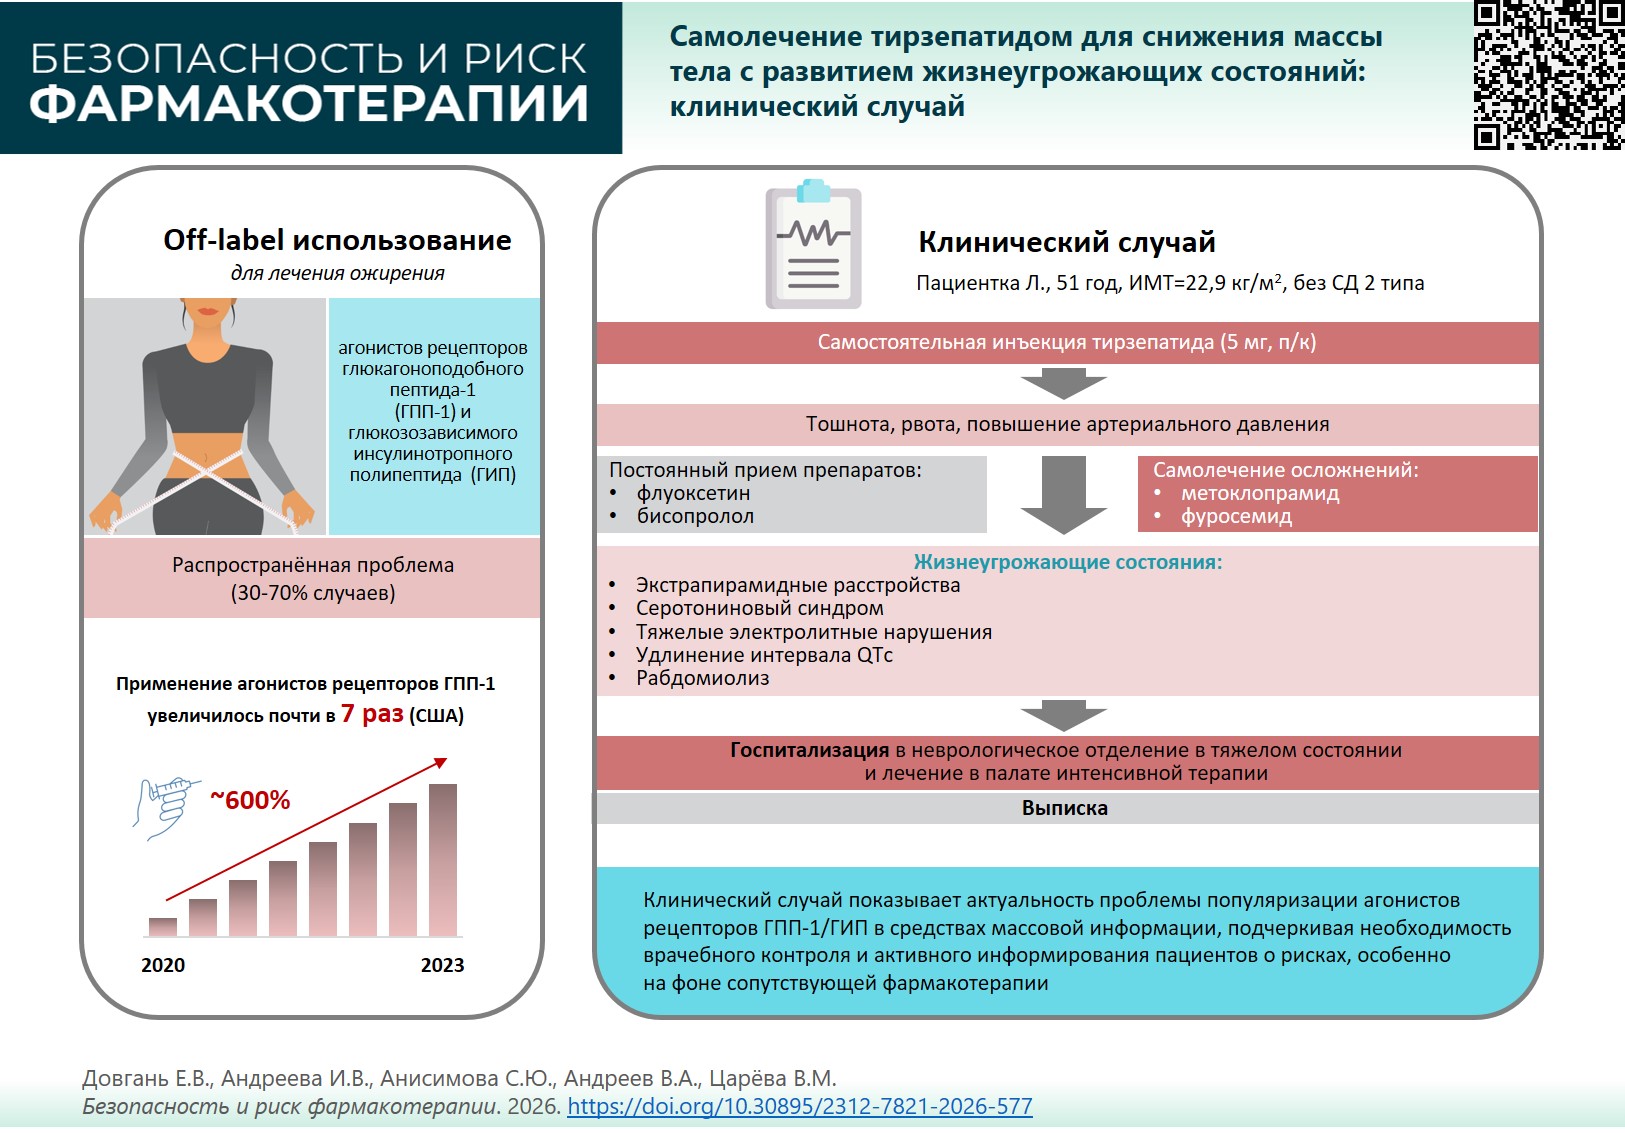
INTRODUCTION. Glucagon-like peptide-1 (GLP-1) and glucose-dependent insulinotropic polypeptide (GIP) receptor agonists are used for the treatment of type 2 diabetes mellitus, obesity, weight reduction, and weight control. Owing to their weight-loss and appetite-suppressant effects, information about these agents has spread widely in the mass media and social networks. A notable aspect of their use worldwide is the widespread practice of self-medication. We present a case of off-label self-medication with the prescription drug tirzepatide.

CASE REPORT. A 51-year-old woman (BMI 22.9 kg/m2, without type 2 diabetes mellitus) self-injected 5 mg of tirzepatide to lose 2–3 kg of body weight. The subsequent self-administration of the prescription medications metoclopramide and furosemide without consulting a physician to relieve nausea, vomiting, and elevated blood pressure led to adverse drug interactions with fluoxetine and bisoprolol, which the patient was taking regularly, and resulted in multiple life-threatening conditions (extrapyramidal disorders, serotonin syndrome, severe electrolyte disturbances, QTc interval prolongation, and rhabdomyolysis) requiring hospitalization.

CONCLUSIONS. Self-medication with tirzepatide at an inadequately high starting dose of 5 mg was the trigger that initiated a cascade of predictable but severe adverse drug reactions. The subsequent uncontrolled use of prescription medications to relieve the symptoms without adherence to dosage regimens and frequency of administration, as well as without consideration of potential drug interactions, led to the development of life-threatening conditions. This clinical case highlights the problem of popularization of GLP-1/GIP receptor agonists in the mass media and underscores the need for physician supervision and proactive patient education about the risks, especially in the presence of concomitant pharmacotherapy.

OPTIMIZING PHARMACOTHERAPY: REAL-WORLD DATA, SAFETY, NEW APPROACHES

290-301 174
Abstract

INTRODUCTION. Generalized infections and rising antimicrobial resistance necessitate the search for alternative therapeutic strategies, one of which is phage therapy. However, two fundamentally different models of its use for sepsis and bacteremia have emerged globally. A critical comparison of these models will help identify potential future directions for phage therapy in Russia.

AIM. The aim of this study was to identify, based on a comparative analysis of clinical-pharmacological and regulatory models for bacteriophage use in the Russian Federation and internationally, key barriers limiting the use of phage therapy for generalized infections, and to determine priority areas for expanding the use of phage therapy for these conditions in Russia.

DISCUSSION. A review of scientific publications in the MEDLINE and eLIBRARY.RU databases (up to December 2025), data from the State Register of Medicines of the Russian Federation, the international registry ClinicalTrials.gov, and regulatory documents was conducted. It was shown that in the United States and Europe phage therapy is implemented mainly in the form of personalized highly purified preparations for intravenous administration within the framework of “expanded access” programs. Successful clinical cases in infectious processes caused by Acinetobacter baumannii, Enterococcus faecium, and Staphylococcus aureus demonstrate the potential of the method. At the same time, its critical limitations have been identified: the impossibility of use for acute sepsis due to the lengthy period of cocktail selection (28–386 days); inefficiency due to titer instability (which led to the termination of the PhagoBurn study) and immune neutralization of bacteriophages. In the Russian Federation, 14 commercial bacteriophage preparations are registered, 11 of which are officially approved for use in generalized infections, but their use is only permitted orally, topically, and rectally; parenteral administration is not provided for by regulations. Individual selection of phage cocktails is not permitted by law; there are no “expanded access” mechanisms; no specialized randomized trials have been conducted in Russia. A comparative analysis identified the main barriers limiting the use of phage therapy: regulatory (the registration system requires new randomized clinical trials for any change in composition) and technological (lack of highly purified forms for intravenous administration, titer instability).

CONCLUSIONS. To expand the clinical use of bacteriophages for generalized infections in the Russian Federation, the following areas are proposed: development of highly purified forms for intravenous administration (and/or demonstration of the efficacy of the oral route in large studies), regulation of procedures for personalized selection of cocktails for a patient-specific isolate, and adaptation of the regulatory framework for the rapid modification and registration of bacteriophage cocktail compositions.

302-319 589
Abstract

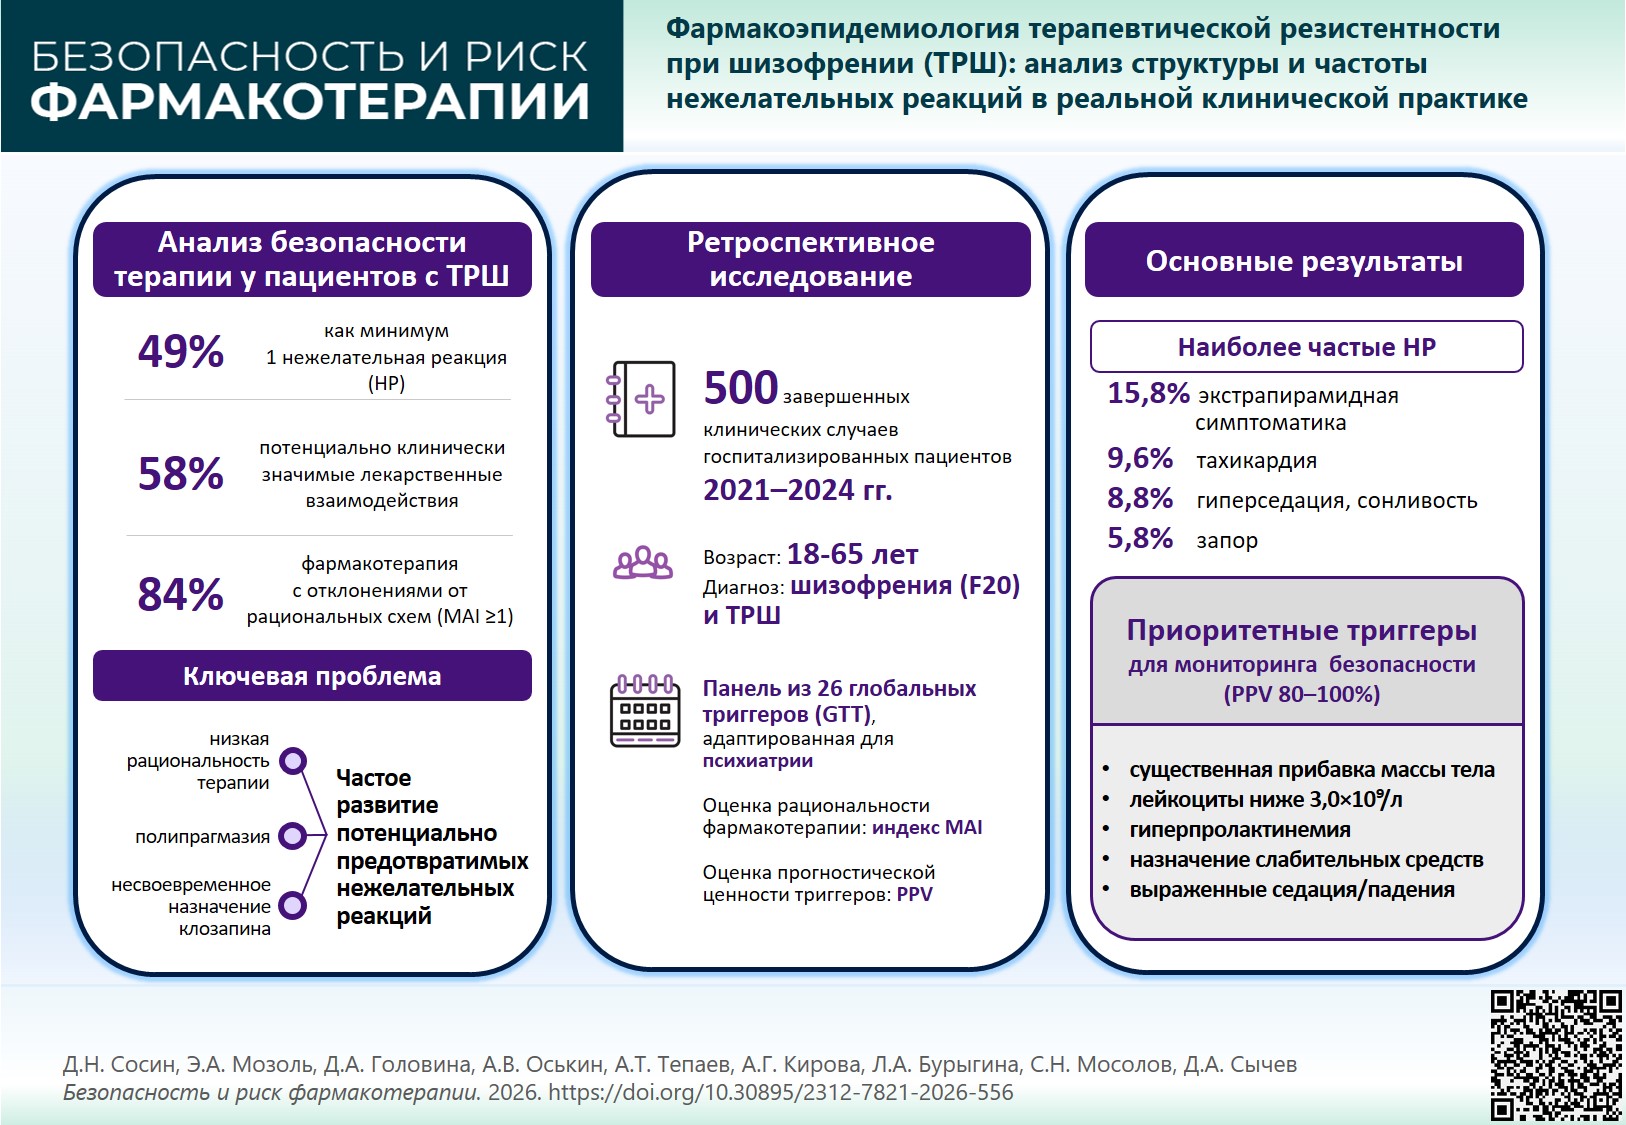
INTRODUCTION. Treatment-resistant schizophrenia (TRS) represents one of the most challenging clinical problems in psychiatry. Clozapine remains the only antipsychotic with proven efficacy for TRS; however, in real-world clinical practice, patients frequently receive combinations of antipsychotic medications, which increases the risk of adverse drug reactions (ADRs). Monitoring the safety of therapy in TRS is of high clinical significance.

AIM. To analyze the safety profile of psychopharmacotherapy in patients with TRS in real-world clinical practice using a custom panel of global triggers adapted for psychiatric inpatient settings, with the aim of optimizing treatment strategies for resistant cases and selecting triggers for inclusion in an active adverse drug reaction monitoring system.

MATERIALS AND METHODS. A retrospective pharmacoepidemiological study was conducted of 500 completed clinical cases of patients with TRS admitted to a psychiatric hospital between 2021 and 2024. ADRs were identified using the global triggers method and classified by type, severity, preventability, and probability of causal relationship. The rationality of pharmacotherapy (assessed using the Medication Appropriateness Index, MAI) and the positive predictive value (PPV) of the triggers were evaluated.

RESULTS. ADRs were identified in 48.8% of patients, most commonly extrapyramidal disorders (15.8%), tachycardia (9.6%), and increased sedation (8.8%). Potentially clinically significant drug interactions were noted in 58.4% of patients. Only 15.6% of patients received rational therapy, while 84.4% showed deviations from recommended pharmacotherapy regimens. Clozapine was prescribed in a timely manner in only 31.6% of patients; in 48.0%, documentation of prescription timing was absent. Maximum PPV values (80–100%) were characteristic of triggers reflecting clinical and laboratory changes: significant weight gain, decreased leukocyte levels, hyperprolactinemia, laxative prescription, and pronounced sedation. Moderate predictive value (36–51%) was demonstrated by triggers associated with concomitant therapy (β-blockers, antidiarrheal and antihistamine agents). Low specificity (PPV 2–20%) was noted for triggers reflecting pharmacotherapy changes (drug discontinuation or dose reduction, prescription and dose adjustment of extrapyramidal symptom correctors). The least informative trigger (PPV 2.0%) was “irrational drug combinations”.

CONCLUSIONS. Psychopharmacotherapy in patients with TRS in psychiatric inpatient settings was characterized by a high frequency of ADRs, substantial prevalence of clinically significant drug interactions, and low prescribing rationality. Triggers reflecting clinical-laboratory changes (significant weight gain, decreased leukocyte levels, hyperprolactinemia, laxative prescription, and pronounced sedation) demonstrated the greatest predictive value and may be recommended for prioritized inclusion in an active safety monitoring system for psychopharmacotherapy in TRS. To optimize treatment strategies for resistant cases, implementation of algorithms for early identification of treatment resistance is necessary, enabling timely clozapine prescription, alongside the use of standardized tools for assessing the rationality of combination therapy.

320-330 524
Abstract

INTRODUCTION. Validated tools for assessing the quality and safety of pharmacotherapy, widely used for scientific and expert purposes, have proven effective in improving treatment quality and optimizing costs. However, their application in routine clinical practice is often limited by the complexity of the assessment procedure and interpretation of results, as well as the lack of adaptation to national clinical guidelines. Therefore, the development of a comprehensive method based on a qualitative and quantitative assessment of pharmacotherapy compliance with clinical guidelines and the criteria of efficacy, rationality, and safety remains relevant.

AIM. To develop and pilot-test an adapted tool, the Pharmacotherapy Assessment Card (the Card), for standardized qualitative and quantitative assessment of pharmacotherapy.

MATERIALS AND METHODS. The basis of the Card was Form No. 313/u, approved by Order No. 494 of the Ministry of Health of the Russian Federation dated October 22, 2003. For quantitative assessment of the criteria, additional tools were integrated into the Card: the modified Medication Appropriateness Index (MAI) and the GerontoNet scale. Evaluation of drug interactions was performed using the Drug-Drug Interactions database. Pilot testing of the Card was conducted using 80 medical records of patients in a multidisciplinary hospital.

RESULTS. The Pharmacotherapy Assessment Card includes 8 criteria for qualitative and quantitative assessment of pharmacotherapy, derived by comparing and integrating criteria from various international validated scales. For example, to objectively assess the criterion “risk of adverse drug reactions,” the GerontoNet scale was applied with a threshold value of ≥4 points. Pilot testing confirmed the applicability of most criteria. The mean assessment time was 90 minutes (decreasing with experience). The integral assessment showed that pharmacotherapy met the rationality criteria in 19.2% of cases (score 6–7), insufficient compliance with criteria was found in 45.2% (score 8–10), partial compliance with criteria in 35.6% (score 11–13), and there were no cases of complete non-compliance with criteria (score 14–16).

CONCLUSIONS. The developed Pharmacotherapy Assessment Card represents a practical tool that combines qualitative and quantitative metrics based on international standardized methods. The tool enables both a quantitative score-based result and a structured conclusion with recommendations for therapy optimization. Further prospective validation of the Pharmacotherapy Assessment Card is planned to confirm reliability and establish statistically justified threshold values for each criterion.

331-345 134
Abstract

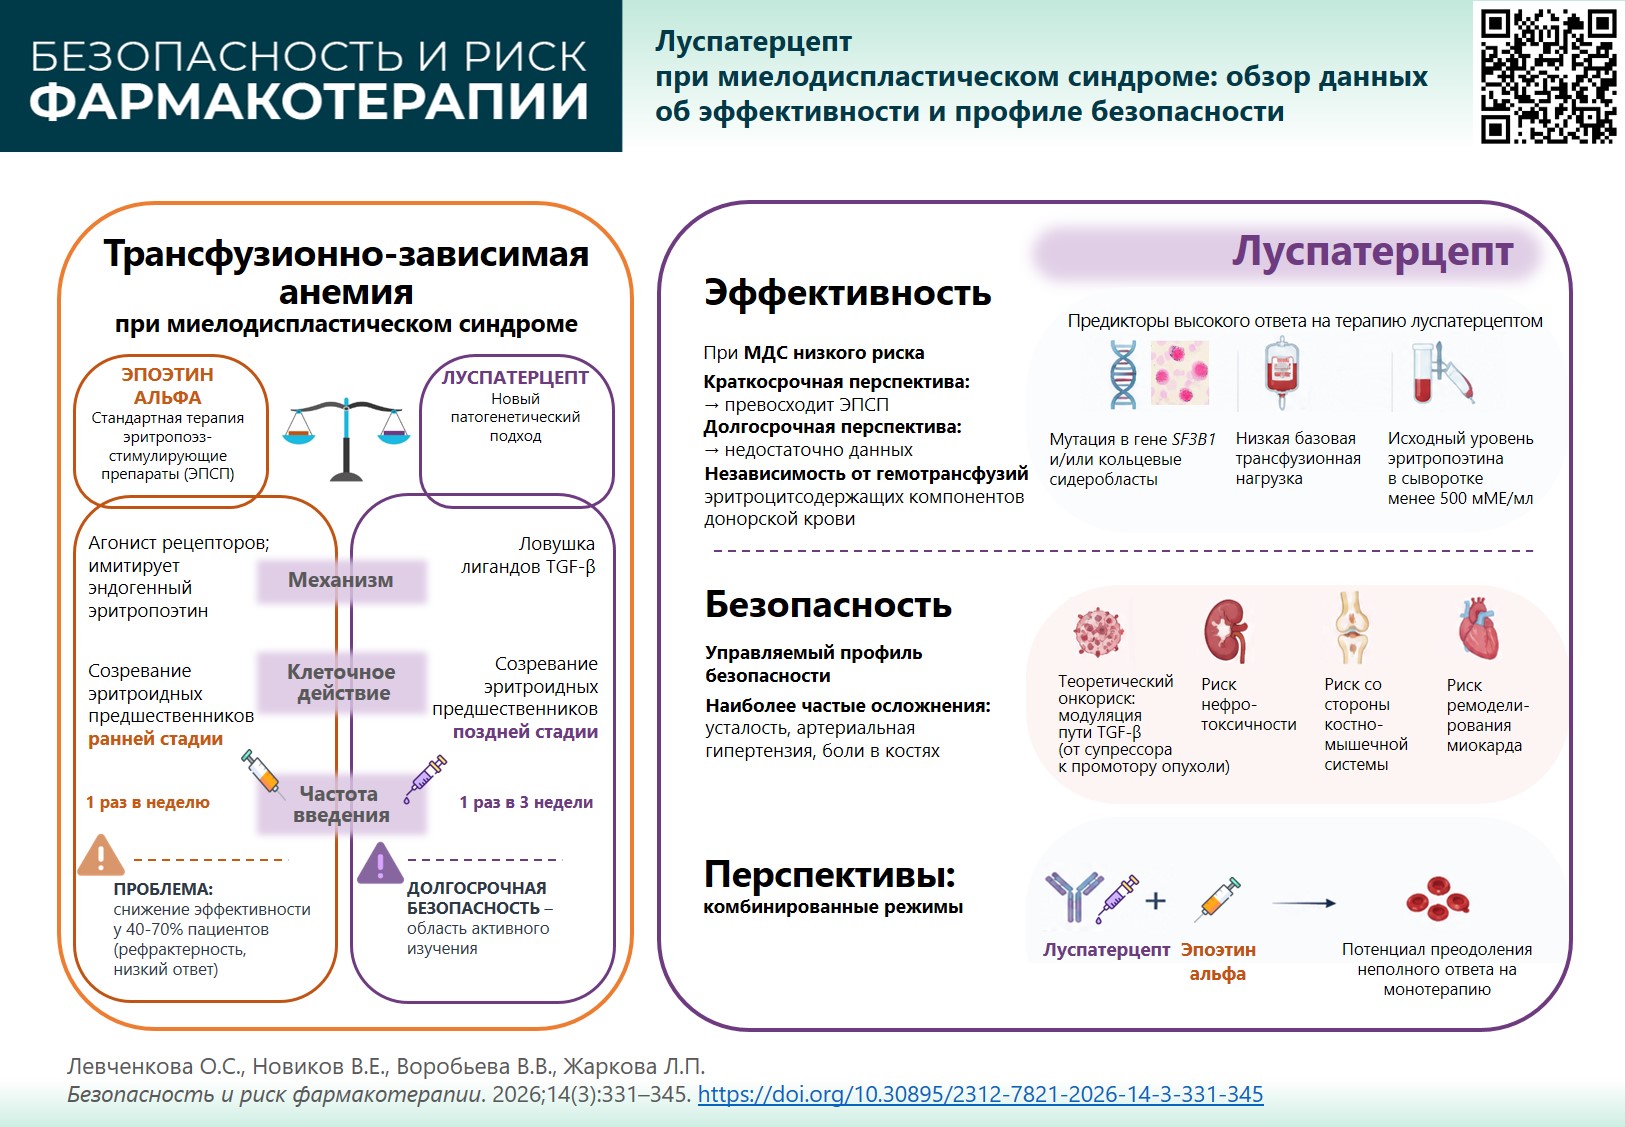
INTRODUCTION. Transfusion-dependent anemia in myelodysplastic syndrome (MDS) is associated with severe complications and reduced survival, with up to 70% of patients being refractory to standard therapy with erythropoiesis-stimulating agents (ESAs). The approval of luspatercept, an inhibitor of the TGF-β signaling pathway, has introduced a novel approach to the pathogenesis-based treatment of anemia; however, accumulating real-world data necessitate a critical evaluation of the drug’s specific delayed risks and refinement of patient stratification algorithms.
AIM. To analyze clinical and postmarketing data on the efficacy, safety, and risks of luspatercept in MDS to refine clinical approaches to therapy and the safety profile of luspatercept.
DISCUSSION. Analysis of data from randomized controlled trials (MEDALIST, COMMANDS) and real-world clinical practice confirms a significant reduction in transfusion dependence and improvement in hemoglobin response
during luspatercept therapy in patients with lower-risk MDS, particularly in the presence of ring sideroblasts, SF3B1 mutations, and an erythropoietin level <500 mIU/mL. At the same time, ESAs remain the first-line agents
in patients without ring sideroblasts, and the routine use of luspatercept as initial therapy for all patients is premature due to insufficient data on long-term clinical benefits. The drug’s safety profile necessitates continuous
monitoring of adverse events: in addition to frequent complications (fatigue, arterial hypertension, and bone pain), special attention should be paid to the risks of nephrotoxicity, delayed remodeling of bone, cartilage, and muscle tissues, as well as the theoretical oncological risk arising from the dual role of the TGF-β signaling pathway in carcinogenesis. A promising direction for overcoming resistance to and incomplete response to monotherapy
is the combination of luspatercept with epoetin alfa, which enhances hematologic response.
CONCLUSIONS. Luspatercept is an effective and pathogenetically substantiated therapeutic option for anemia in patients with myelodysplastic syndrome with ring sideroblasts. However, its use requires strict patient stratification based on molecular genetic biomarkers (the presence of ring sideroblasts, SF3B1 mutations) and endogenous erythropoietin levels. The development of monitoring algorithms for luspatercept-specific adverse events (nephrotoxicity, changes in bone and cartilage tissue) and the justification of combination therapy strategies with ESAs will enhance the hematologic response and control the delayed risks of pharmacotherapy within the rational drug use.

346-354 425
Abstract

INTRODUCTION. In geriatrics, the practice of empirical symptomatic use of medications without establishing a definitive diagnosis has become entrenched, while clinical guidelines are focused on specific disease entities. The updated document “Alternatives to Specific Medications According to the American Geriatrics Society Beers Criteria (2023)," published in 2025 by the American Geriatrics Society, provides recommendations with a high level of evidence. However, their direct transfer into Russian clinical practice is limited by the registration status of certain medications in Russia.

AIM. To assess the feasibility and propose a strategy for implementing the list of alternative medications for common clinical conditions in older adults, developed by the American Geriatrics Society expert panel, into Russian clinical practice.

MATERIALS AND METHODS. An analysis of the 2025 American Geriatrics Society recommendations was performed, with an assessment of the compliance of medicinal products with the State Register of Medicines and with the clinical guidelines of the Russian Federation.

RESULTS. The expert panel of the American Geriatrics Society selected 30 criteria for which alternative medications were proposed for the treatment of 21 conditions in older adults: allergic rhinitis, pruritus, pain, diabetes mellitus, weight loss, atrial fibrillation, venous thromboembolism, heart failure, arterial hypertension, insomnia, anxiety, delirium, Parkinson’s disease, tardive dyskinesia, gastroesophageal reflux disease, gastroparesis, intestinal cramping, diarrhea, constipation, nocturia, genitourinary syndrome of menopause, and recurrent urinary tract infections. Of the recommended international nonproprietary names of medicinal products, 80% are registered in the Russian Federation. For medicinal products not approved for use in Russian clinical practice, therapeutic equivalents that comply with Russian clinical guidelines were identified, and their use in geriatric patients was justified for insomnia, tardive dyskinesia, constipation, and menopausal syndrome.

CONCLUSIONS. Most alternative medications recommended by the American Geriatrics Society in 2025 are approved for use in the Russian Federation. For the unregistered medicinal products used to treat insomnia, tardive dyskinesia, constipation, and menopausal syndrome in older adults, replacement with therapeutic equivalents that have proven efficacy and a favorable safety profile is recommended in accordance with Russian clinical guidelines.

DRUG SAFETY INFORMATION FROM REGULATORY AUTHORITIES

Announcements

2026-09-01

Правовые основы передачи генетических данных человека

С 1 сентября 2026 года вступил в силу Федеральный закон от 20.02.2026 № 43-ФЗ, который вносит изменения в регулирование генно-инженерной деятельности и устанавливает правовые основы передачи генетических данных за пределы России.

More Announcements...


Creative Commons License
This work is licensed under a Creative Commons Attribution 4.0 License.